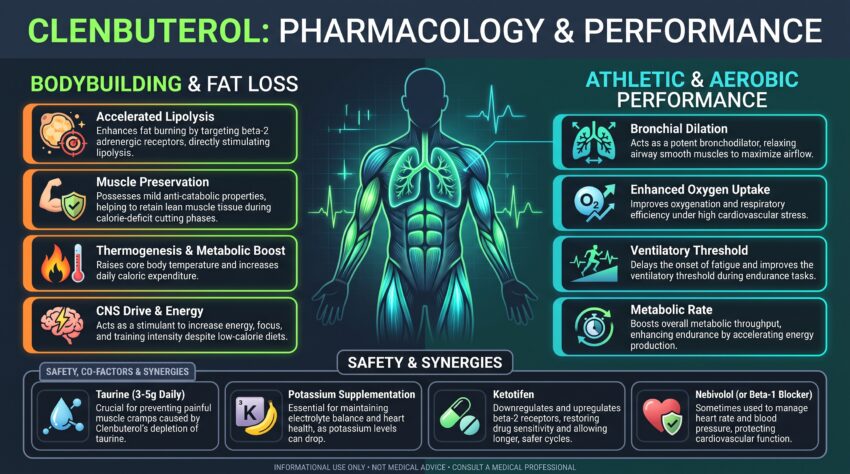
Classification: beta_2-Adrenergic Agonist / Non-Steroidal Sympathomimetic (Non-Peptide / Non-Anabolic Steroid Compound)
Clenbuterol Application Matrix
| Feature | Bodybuilding & Physique Prep | Athletic Performance & Endurance |
| Primary Goal | Accelerated lipolysis & dry, vascular contest conditioning | Increased aerobic capacity, airway dilation, and time-to-exhaustion |
| Secondary Goal | Muscle preservation during steep caloric deficits | Anti-catabolic protection during high-volume training blocks |
| Target Pathway | beta_2-adrenoceptor activation -> cAMP -> PKA -> HSL | Bronchial smooth muscle relaxation & optimized alveolar gas exchange |
| Dosing Range | 20 mcg – 120 mcg daily (titrated upward) | 10 mcg – 40 mcg daily (low dose for bronchodilation) |
| Key Synergies | Taurine, Potassium, Ketotifen, T3 (Cytomel), Nebivolol | Taurine, Electrolyte complex, Nebivolol |
| Primary Constraint | Rapid beta_2-receptor downregulation (~14 days) | Tremors, elevated resting heart rate, cardiotoxicity risk at higher doses |
ADME Profile (Absorption, Distribution, Metabolism, Excretion)
- Absorption: Rapidly and completely absorbed following oral administration, with systemic bioavailability reaching 70%–80%. Peak plasma levels occur within 2–3 hours. Food does not significantly impair total absorption.
- Distribution: Extensively distributed throughout body tissues due to high lipid solubility. Crosses the blood-brain barrier and concentrates heavily in lungs, vascular smooth muscle, liver, and skeletal muscle tissue.
- Metabolism: Metabolized in the liver via glucuronidation and mono-oxygenation pathways. Unlike many sympathomimetics, Clenbuterol is not a substrate for catechol-O-methyltransferase (COMT) or monoamine oxidase (MAO), contributing to its exceptionally long active duration.
- Excretion: Primarily excreted through the kidneys (approx. 40%–50% as unchanged parent drug and remaining balance as inactive metabolites). Elimination follows biphasic clearance with a prolonged terminal phase.
Quick Reference Guide
- Mechanism / Pathways:
- beta_2-Adrenergic Activation: Selectively binds to beta_2-adrenoceptors on adipocytes, stimulating adenylyl cyclase to elevate intracellular cyclic AMP (cAMP).
- Lipolysis Cascade: Elevated cAMP activates Protein Kinase A (PKA), which phosphorylates Hormone-Sensitive Lipase (HSL) and perilipins, driving the breakdown of stored triglycerides into free fatty acids (FFAs) for oxidation.
- Thermogenesis & Uncoupling: Increases basal metabolic rate (BMR) by up to 10%–20% through hyperthermia and induction of Uncoupling Proteins (UCP-1/UCP-3) in metabolic tissues.
- beta_2-Mediated Anti-Catabolism: Stimulates the Calpastatin/Calpain pathway and Akt/mTOR signaling in skeletal muscle, inhibiting ubiquitin-proteasome protein degradation.
- Genomic vs. Non-Genomic: Dual Action.
- Non-Genomic: Acute, immediate bronchodilation, cardiac acceleration, and lipolytic enzyme phosphorylation via cAMP/PKA signaling within minutes to hours.
- Genomic: Downregulation/desensitization of beta_2-adrenoceptor gene expression after continuous exposure; suppression of proteolytic enzyme genes (Calpains/MuRF1) in skeletal muscle.
- Key Benefits:
- Potent Fat Oxidation: Direct, non-thyroidal, non-androgenic acceleration of fatty acid mobilization.
- Muscle Preservation (Anti-Catabolic): Protects nitrogen retention and lean tissue mass during extreme caloric restriction.
- Bronchodilation & Oxygen Uptake: Relaxes bronchial smooth muscle, improving ventilatory threshold and pulmonary airflow.
- Central Nervous System Drive: Increases alertness and neural drive during low-carbohydrate prep phases.
- Dosing Range:
- Starting Dose: 20 mcg daily (assess tolerance for 2–3 days).
- Standard Maximum Dose: 80 mcg – 120 mcg daily (split or single morning dose). Do not exceed 140 mcg daily.
- Dosing Strategies:
- 2 Weeks On / 2 Weeks Off Protocol: Run Clenbuterol for 14 days with progressive 20 mcg upward titration every 3–4 days. Pause for 14 days (using an alternative non-beta_2 burning agent like OTC thermogenics or Yohimbine) to allow beta_2-receptors to resensitize naturally.
- Continuous Protocol with Ketotifen: Run Clenbuterol continuously for 4–6 weeks by adding Ketotifen (1 mg – 2 mg at bedtime) starting on day 10–14 to upregulate beta_adrenoceptor density and prevent desensitization.
- Half-Life: Approximately 36 to 39 hours (requires 4–5 days to clear completely from systemic circulation after cessation).
- Peak Saturation: Reaches peak plasma concentration (C_max) in 2–3 hours. Steady-state plasma levels are achieved within 3–4 days of daily administration.
- Duration of Use: 2 to 6 weeks maximum per cycle. Extended uninterrupted use beyond 6 weeks significantly elevates cardiotoxicity risks without additional fat loss benefits.
- Detectability: Prohibited by WADA under Section S3 (beta_2 Agonists). Detectable in urine for 10–14+ days post-administration; detectable in hair samples for months.
Technical Deep-Dive
1. Thermogenesis & Fat Oxidation
Clenbuterol bypasses the central nervous system reliance seen with classical ephedrine/caffeine formulations by acting as a direct receptor agonist. By directly occupying beta_2 receptors on the surface of subcutaneous and visceral fat cells, Clenbuterol maintains continuous intracellular cAMP signaling. This increases body temperature by 0.5°C to 1.0°C, steadily ramping up daily total energy expenditure (TEE) independent of voluntary physical activity.
2. Anti-Catabolic & Muscle Preservation Mechanics
While animal models demonstrate actual skeletal muscle hypertrophy at high dosages, human dosing achieves an anti-catabolic (nitrogen-sparing) effect. Clenbuterol increases intracellular cAMP levels in skeletal muscle fibers, which upregulates Calpastatin—an endogenous inhibitor of Calpain proteases. Furthermore, beta_2 stimulation subtly modulates the Akt/mTOR pathway, slowing down muscle protein breakdown (MPB) even when blood insulin and glycogen levels are severely depleted during contest preparation.
3. Aerobic Capacity & Airway Conductance
Originally synthesized as a pharmaceutical bronchodilator for asthma treatment, Clenbuterol acts on bronchial smooth muscle cells via beta_2 receptor coupling. This causes immediate relaxation of the airway passages, reducing airway resistance and increasing total lung capacity. Athletes experience higher oxygen saturation during steady-state cardiovascular work and a delayed onset of hypercapnic fatigue.
Safety, Side Effects & Contraindications
Common & Dose-Dependent Side Effects
- Muscular Tremors & Shakes: Involuntary fine motor tremors (especially in hands) caused by motor nerve terminal stimulation.
- Severe Muscle Cramps: Resulting from rapid cell membrane transport shifts that deplete intracellular Taurine and Potassium.
- Cardiovascular Strain: Tachycardia (elevated resting heart rate), palpitations, elevated systolic blood pressure, and cardiac arrhythmia.
- CNS Over-Stimulation: Insomnia, acute anxiety, restlessness, and headaches.
- Long-Term Cardiotoxicity Risk: Prolonged excessive exposure induces cardiac myocyte necrosis and Left Ventricular Hypertrophy (LVH).
Absolute Contraindications
- Structural heart disease, coronary artery disease, or pre-existing cardiac arrhythmias.
- Uncontrolled hypertension.
- Hyperthyroidism / Thyrotoxicosis.
- Severe anxiety, panic disorders, or active psychiatric conditions.
- Concomitant use of monoamine oxidase inhibitors (MAOIs) or cardiotoxic pharmaceuticals.
Synergistic Supplements & Countermeasures
To maximize safety, mitigate severe side effects, and extend compound efficacy, the following adjunctive protocols are mandatory:
- Taurine (3g – 5g daily): Mandatory Countermeasure. Clenbuterol inhibits intestinal taurine transport and depletes skeletal muscle/cardiac taurine concentrations. Without exogenous Taurine, users experience debilitating muscle cramps.
- Potassium (500mg – 1000mg supplemental daily + food): beta_2 agonists drive extracellular potassium directly into intracellular space, causing transient hypokalemia. Sustained potassium intake prevents cardiac dysrhythmias and peripheral cramping.
- Ketotifen (1mg – 2mg taken at bedtime): A second-generation antihistamine that upregulates beta_2 adrenoceptors, reversing receptor desensitization and allowing Clenbuterol to remain effective past the 14-day mark.
- Nebivolol (2.5mg – 5mg daily): A highly selective beta_adrenergic blocker. Nebivolol selectively controls elevated heart rate and blood pressure without blocking the beta_2 receptors required for Clenbuterol’s lipolytic and bronchodilatory action.
- Electrolyte & Hydration Complex: Minimum 4–5 liters of water daily to support vascular volume during increased thermogenesis.
What to Avoid
- Yohimbine / Ephedrine / High-Dose Caffeine: Stacking Clenbuterol with potent alpha_2 antagonists or heavy central nervous system stimulants causes compounding cardiovascular strain, dangerous spikes in blood pressure, and acute arrhythmia risk.
- Late-Day Dosing: Due to the 36-hour half-life, taking Clenbuterol after 12:00 PM will severely disrupt deep sleep and autonomic recovery architecture.
- Severe Dehydration / Dry Saunas: Combined with Clenbuterol-induced sweating and electrolyte shifts, acute dehydration drastically heightens cardiac toxicity and severe muscle cramping.
General Coaching Notes
Clenbuterol remains one of the most powerful non-hormonal fat oxidation tools available in advanced bodybuilding and athletic coaching, but its power requires strict management. It is not a casual fat burner, nor is it a substitute for an established caloric deficit. Clenbuterol acts as an accelerator, pulling body fat down when natural metabolic adaptations begin to stall late in a prep or cutting phase.
The single biggest error in managing Clenbuterol is attempting to force results by escalating the dosage too rapidly. Because of its long 36-hour half-life, Clenbuterol accumulates in tissue over several days. A dose that feels manageable on Day 1 can produce severe tremors and tachycardia by Day 4 as steady-state plasma concentration is achieved. Gradual titration is essential.
From a health preservation standpoint, cardiovascular protection must take priority. Heart rate monitors should be utilized to track baseline resting HR, which should not be allowed to chronically exceed 90–95 BPM. Enforcing the mandatory Taurine + Potassium protocol eliminates 90% of user complaints regarding painful cramps, while incorporating Nebivolol offers a sophisticated layer of cardiac protection for elite athletes operating at the higher end of the dosing spectrum.