Classification: Glycoprotein Hormone / Luteinizing Hormone (LH) Mimetic (Injectable Peptide Hormone)
HCG Application Matrix
| Feature | On-Cycle Maintenance & PCT Preparation | TRT & Fertility Restoration |
| Primary Goal | Preventing/reversing testicular atrophy and maintaining Leydig cell sensitivity | Restoring intratesticular testosterone (ITT) and supporting spermatogenesis |
| Secondary Goal | Preserving neurosteroid precursor pathways (pregnenolone, DHEA) | Restoring testicular volume and physiological hormone production |
| Target Pathway | LH/hCG receptor (LHCGR) activation on Leydig cells -> cAMP activation | LHCGR activation + FSH synergism for Sertoli & Leydig cell stimulation |
| Dosing Range | 250 IU – 500 IU SubQ twice weekly (or 250 IU EOD) | 500 IU – 1,500 IU SubQ 2–3 times weekly (often paired with HMG/FSH) |
| Key Synergies | Arimidex/Aromasin (for e2), TRT / AAS cycles, Zinc, CoQ10 | HMG (Human Menopausal Gonadotropin), L-Carnitine, Vitamin E, Selenium |
| Primary Constraint | Intratesticular aromatization (high e2 spike risk at high doses) | Pituitary suppression via negative feedback (suppresses endogenous LH/FSH) |
ADME Profile (Absorption, Distribution, Metabolism, Excretion)
- Absorption: Administered via Subcutaneous (SubQ) or Intramuscular (IM) injection. SubQ absorption is slightly slower but achieves nearly identical total bioavailability (~90%+). Peak serum concentrations (Cmax) occur within 6 to 12 hours post-SubQ injection (12 to 24 hours post-IM).
- Distribution: Rapidly distributes into systemic circulation and extracellular space, accumulating selectively in target tissues expressing LH/hCG receptors ($LHCGR$), predominantly Leydig cells in male testes and granulosa/theca cells in ovaries.
- Metabolism: Degraded primarily in the kidneys and liver. Approximately 80% of systemic clearance is handled by renal tubular metabolism, where the heterodimeric glycoprotein is cleaved into smaller subunit peptide fragments and free beta-subunit metabolites.
- Excretion: Excreted mainly through the urine. Roughly 10%–12% of the injected dose is excreted as intact, active hCG, with the remainder eliminated as inactive urinary hCG core fragments (hCG\beta cf).
Quick Reference Guide
- Mechanism / Pathways:
- LHCGR Binding: Shares the identical beta-subunit binding site as endogenous Luteinizing Hormone (LH), directly stimulating Leydig cell surface receptors.
- Intratesticular Steroidogenesis: Triggers G-protein-coupled activation of adenylyl cyclase, elevating intracellular cyclic AMP (cAMP) and upregulating Steroidogenic Acute Regulatory (StAR) protein.
- Cholesterol Translocation: Accelerates the transport of cholesterol into the inner mitochondrial membrane, converting it to pregnenolone and driving endogenous Intratesticular Testosterone (ITT) synthesis.
- Genomic vs. Non-Genomic: Dual Action.
- Non-Genomic: Acute, rapid activation of cAMP signaling and immediate StAR-mediated cholesterol translocation within hours of administration.
- Genomic: Long-term transcriptional upregulation of key steroidogenic enzymes (CYP11A1, CYP17A1, 17 beta-HSD) and maintenance of structural Leydig cell mass.
- Key Benefits:
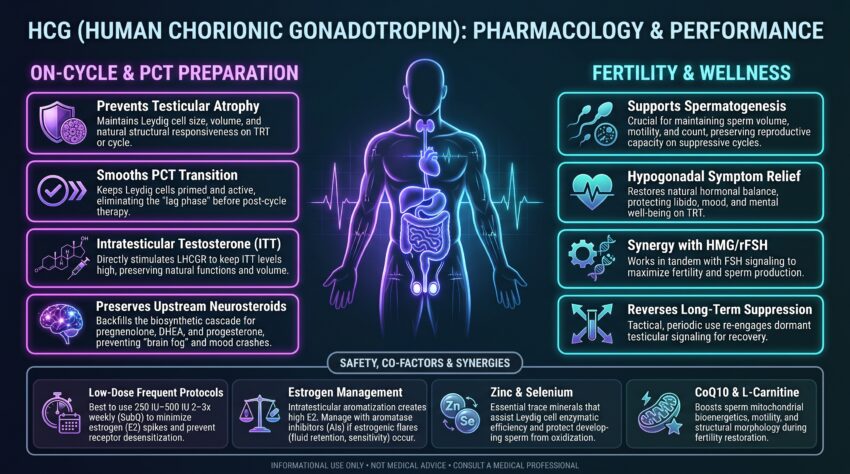
- Prevents & Reverses Testicular Atrophy: Restores normal testicular size, firmness, and vascularity during suppressive androgen protocols.
- Preserves Fertility & Sperm Count: Maintains Intratesticular Testosterone (ITT) levels (which are 50–100x higher than serum testosterone), essential for continuous spermatogenesis.
- Backfills Neurosteroid Pathways: Prevents the “neurosteroid void” by maintaining upstream hormones like Pregnenolone, Progesterone, and DHEA, which are shut down during exogenous hormone use.
- Smooths Post-Cycle Transition: Keeps Leydig cells primed and responsive, eliminating the lag phase when transitioning into formal Post-Cycle Therapy (PCT).
- Dosing Range:
- On-Cycle / TRT Maintenance Dose: 250 IU – 500 IU SubQ twice weekly.
- Fertility Protocol Dose: 500 IU – 1,500 IU SubQ 2–3 times weekly.
- Pre-PCT Blast Kickstart: 500 IU – 1,000 IU EOD for 10–14 days immediately prior to starting SERM therapy.
- Dosing Strategies:
- Low-Dose Frequent Protocol (Preferred): 250 IU administered SubQ every other day (EOD) or 3x/week. Minimizes intratesticular estrogen spikes and prevents LH receptor desensitization.
- Avoid Megadosing: Infrequent large boluses (e.g., 2,500 IU – 5,000 IU in a single injection) should be avoided due to severe aromatization and potential downregulation of Leydig cell $LHCGR$ density.
- Half-Life: Biphasic elimination half-life:
- Initial Fast Phase: ~5.6 to 11 hours.
- Terminal Elimination Half-Life: 24 to 36 hours.
- Peak Saturation: Reaches maximum serum levels within 6 to 12 hours post-SubQ administration.
- Duration of Use: Continuous maintenance alongside TRT/cycles, or in 2–4 week tactical blocks for PCT preparation or fertility protocols.
- Detectability: Prohibited by WADA under Section S2 (Peptide Hormones, Growth Factors, Related Substances, and Mimetics). Detectable in urine via immunoassay testing for 7 to 10 days post-injection.
Technical Deep-Dive
1. Intratesticular Testosterone (ITT) & Leydig Cell Preservation
Exogenous androgen use triggers negative feedback on the hypothalamic-pituitary-gonadal (HPG) axis, halting pituitary LH secretion. Without LH signaling, Intratesticular Testosterone (ITT) drops by up to 95%, even if serum testosterone levels remain elevated from injections. Because ITT is the primary driver of spermatogenesis and Leydig cell structural integrity, prolonged suppression leads to Leydig cell atrophy. HCG acts as a direct LH substitute, maintaining high ITT concentrations and keeping the cellular machinery fully operational.
2. The Neurosteroid Backfill Mechanism
The shutdown of LH shuts down the enzyme CYP11A1 (cholesterol side-chain cleavage enzyme) in the testes. This cuts off the body’s primary production of Pregnenolone, the mother precursor for all neurosteroids, including DHEA, Allopregnanolone, and Progesterone. Many athletes on TRT or cycles who experience brain fog, anxiety, or low mood despite high serum testosterone are suffering from this neurosteroid void. HCG restores upstream cholesterol cleavage, backfilling these essential brain-protective neurosteroid pathways.
3. Intratesticular Aromatization Dynamics
Unlike peripheral aromatization (which occurs in adipose tissue and can be managed easily with standard Aromatase Inhibitors), HCG directly stimulates the aromatase enzyme inside the Leydig cells. High doses of HCG cause a rapid spike in intratesticular Estradiol (e2). Because this estrogen is produced inside the testes, standard oral AIs (like Arimidex or Aromasin) are less effective at completely blocking it. Low-dose, high-frequency administration (e.g., 250 IU EOD) is the primary method to control this pathway.
Safety, Side Effects & Contraindications
Common & Dose-Dependent Side Effects
- Estrogenic Flares: Nipple sensitivity, gynecomastia, fluid retention, and elevated blood pressure caused by intratesticular aromatization.
- Acne & Oily Skin: Increased sebum production driven by sudden spikes in endogenous androgen and estrogen production.
- Leydig Cell Desensitization: Chronic overuse of megadoses (>2,500 IU per dose) can cause desensitization of the LHCGR receptor and downregulation of downstream steroidogenic enzymes.
- Pituitary Suppression: HCG itself exerts negative feedback on the pituitary gland. It must be stopped before starting SERMs (Nolvadex/Clomid) during PCT.
Absolute Contraindications
- Known or suspected prostate carcinoma or male breast cancer.
- Undiagnosed testicular masses or active testicular carcinoma.
- Pre-existing severe erythrocytosis / polycythemia.
- Hypersensitivity to gonadotropin preparations.
Synergistic Supplements & Countermeasures
To optimize fertility, manage estrogenic side effects, and protect long-term testicular function, the following protocol should accompany HCG administration:
- Aromatase Inhibitor (Arimidex / Aromasin): Kept on hand to manage systemic e2 elevation if high-dose HCG protocols are required for fertility restoration.
- Zinc Picolinate (30 mg daily) + Selenium (200 mcg daily): Essential trace minerals that support Leydig cell enzymatic efficiency and protect developing spermatozoa from oxidative stress.
- CoQ10 (Ubiquinol 200 mg daily) + L-Carnitine (1,000 mg daily): Improves sperm mitochondrial bioenergetics, motility, and structural morphology during fertility restoration.
- HMG (Human Menopausal Gonadotropin) / rFSH: Combined with HCG in clinical fertility settings to provide direct Follicle-Stimulating Hormone (FSH) signaling to Sertoli cells for maximal sperm production.
What to Avoid
- Running HCG During Active PCT (SERM Phase): Because HCG activates $LHCGR$ and produces systemic testosterone/estrogen, it keeps the pituitary suppressed. HCG must be discontinued before starting Tamoxifen or Clomiphene during PCT.
- High-Dose Injection Boluses: Avoid single injections exceeding 1,500 IU unless explicitly prescribed under acute clinical conditions.
- Storing Reconstituted HCG at Room Temperature: Reconstituted HCG peptide degrades rapidly. It must be stored in the refrigerator (2°C–8°C) and used within 30–60 days.
General Coaching Notes
HCG is one of the most essential tools in modern hormone optimization and physique coaching. The traditional approach of waiting until the end of a long, heavy cycle to blast massive doses of HCG is outdated and counterproductive. Blasting high doses right before PCT spikes estrogen, desensitizes Leydig cells, and delays HPG axis recovery.
The modern gold standard is on-cycle maintenance dosing. By keeping a low dose (250 IU twice weekly or EOD) running throughout a TRT protocol or cycle, the athlete prevents testicular atrophy from ever occurring in the first place. The testes remain full, natural neurosteroid production stays active, and the client maintains baseline testicular responsiveness.
When coaching clients through fertility restoration or PCT preparation, emphasize frequency over volume. Splitting micro-doses across the week keeps blood levels stable, prevents heavy estrogen spikes, and creates an optimal environment for long-term hormonal wellness.